
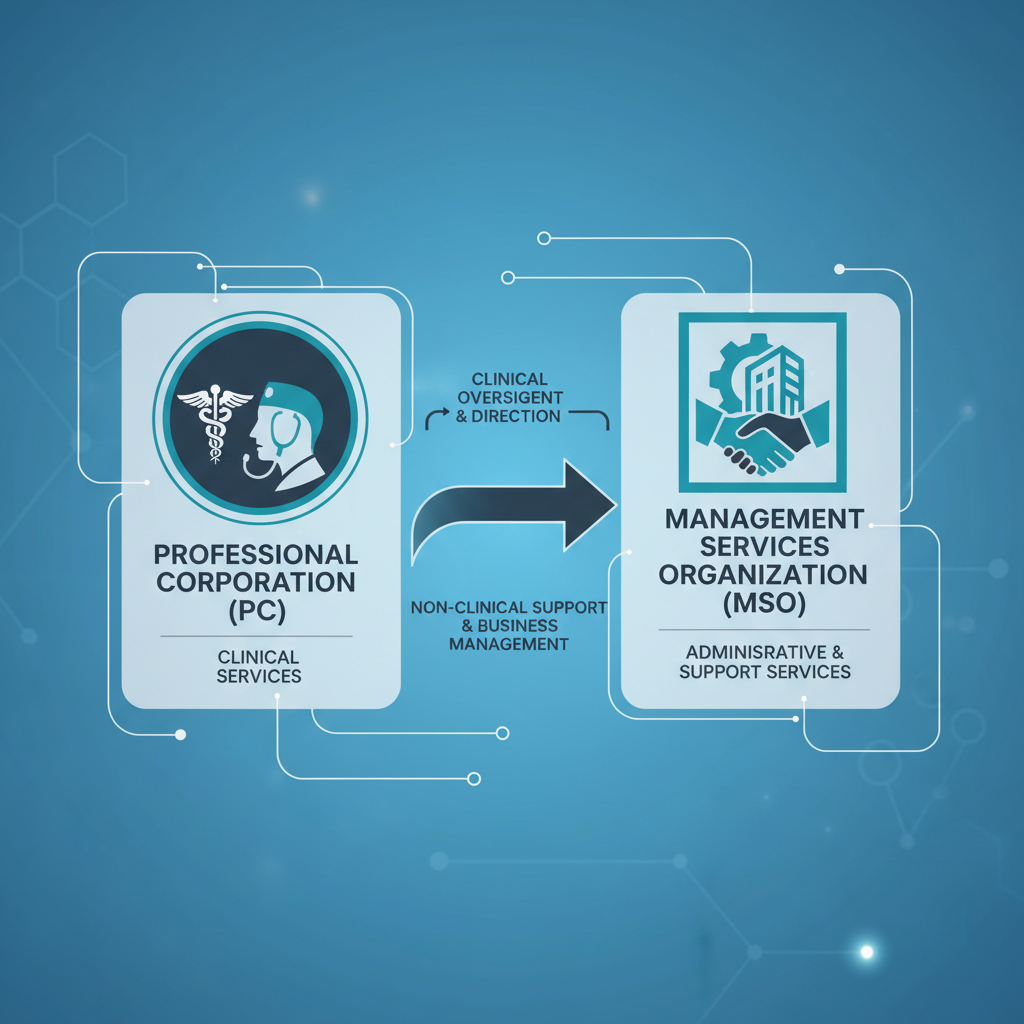
An MSO/PC structure is a healthcare business arrangement in which a management services organization provides non-clinical administrative support to a physician-owned professional corporation, professional association, or other licensed professional entity.
The basic idea is simple: the professional entity provides medical care, and the MSO supports the business operations.
But the legal analysis is not simple. An MSO/PC structure is not automatically compliant just because the parties use the right labels. The question is whether the structure actually preserves professional independence in practice.
If the MSO controls clinical decisions, provider supervision, patient eligibility, prescriptions, medical records, treatment protocols, or the economic substance of the practice, the arrangement may create corporate practice of medicine risk.
What Does an MSO Do in a Healthcare Business?
An MSO, or management services organization, generally provides non-clinical business support to a medical practice or professional entity. Those services may include administrative staffing, scheduling support, bookkeeping, marketing support, technology, vendor coordination, call center support, office management, and other operational services.
The professional entity should remain responsible for medical judgment, patient care, prescriptions, clinical protocols, supervision of licensed professionals, medical records, and other professional decisions.
That separation is the core purpose of the MSO/PC model.
Why Do Healthcare Businesses Use MSO/PC Structures?
Healthcare businesses often use MSO/PC structures because many states restrict or prohibit the corporate practice of medicine. In those states, a general business entity may not be allowed to own a medical practice, employ physicians to provide professional medical services, or control professional medical judgment.
California states the rule directly. Business and Professions Code section 2400 provides: "Corporations and other artificial legal entities shall have no professional rights, privileges, or powers."
New York also limits the practice of medicine to licensed or otherwise authorized persons. New York Education Law section 6522 provides: "Only a person licensed or otherwise authorized under this article shall practice medicine or use the title 'physician'."
The exact rule varies by state. But the compliance issue is consistent: a non-clinical business should not control the practice of medicine.
Can an MSO Own a Medical Practice?
In corporate practice of medicine states, an MSO generally should not own or control the medical practice. The professional entity should be owned and controlled by licensed professionals to the extent required by applicable state law.
The MSO may support the business. It may provide management services. It may help with infrastructure. But it should not be the real medical practice operating behind a professional entity that exists only on paper.
That is where many MSO/PC structures become vulnerable.
A structure may look compliant in the formation documents, but still create risk if the MSO controls the practical operation of the clinical business. Regulators, payors, investors, and litigation opponents will look at substance, not just labels.
What Should the Professional Entity Control?
The professional entity should retain control over professional and clinical decisions. That includes, at minimum, decisions about diagnosis, treatment, prescriptions, provider supervision, clinical protocols, patient care standards, medical records, and clinical judgment.
A management services agreement should make this clear. It should not merely say that the MSO provides "management services." It should identify the MSO's role as non-clinical and preserve the professional entity's control over clinical matters.
This distinction is becoming even more important. California SB 351 added Health and Safety Code section 1191, which restricts private equity groups and hedge funds involved with physician or dental practices from interfering with professional judgment and from exercising control over specified practice functions.
What Should an MSO Agreement Avoid?
An MSO agreement should avoid giving the MSO control over clinical care. It should also avoid language that makes the MSO appear to own the patients, direct the providers, control treatment, or determine medical outcomes.
Common problem areas include provisions giving the MSO approval rights over provider hiring or firing based on clinical competency, control over clinical protocols, control over medical records, control over prescriptions, control over patient eligibility for treatment, or control over the professional entity's clinical policies.
Payment terms also require careful drafting. A management fee that looks like a percentage of professional revenue, a reward for referrals, a payment tied to prescription volume, or a fee tied directly to the value or volume of medical services may create additional regulatory concerns.
Why Patient-Facing Disclosures Matter
The legal documents are only part of the structure. The website, intake flow, marketing materials, consent forms, refund policies, and patient communications also matter.
If the website says that the MSO "provides medical consultations," "prescribes medication," or "employs medical providers," that language may undercut the structure. Patient-facing materials should accurately describe which entity provides medical services and which entity provides administrative, technology, or management support.
This is especially important for telehealth companies, medical spas, cash-pay platforms, subscription healthcare businesses, and healthcare startups that operate under a single brand.
Common MSO/PC Structure Mistakes
Many MSO/PC problems come from over-control. The MSO wants to protect the business, brand, customer experience, and economics. That is understandable. But in healthcare, too much control can create legal risk.
Common mistakes include treating the professional entity as a nominee, giving the MSO final approval over clinical decisions, using website language that suggests the MSO provides medical care, tying management fees too closely to professional revenue, failing to distinguish administrative services from medical services, and using stock transfer or termination rights that make the physician owner look independent in name only.
Another common mistake is waiting too long to address the structure. It is much easier to build the structure correctly before launch than to fix it after patients have been treated, money has flowed, providers have been contracted, and marketing claims have been published.
What Should Healthcare Businesses Review Before Launch?
Before launching an MSO/PC healthcare business, the parties should review the full structure, not just the management agreement. That includes entity formation, ownership, governance, management services, provider agreements, patient-facing disclosures, website language, marketing claims, payment flows, refund policies, prescription workflows, privacy practices, and state-specific professional ownership rules.
The review should also consider whether the business is operating in one state or multiple states. Multi-state telehealth businesses require special attention because corporate practice of medicine rules, professional entity rules, telehealth rules, prescribing rules, and disclosure requirements vary by state.